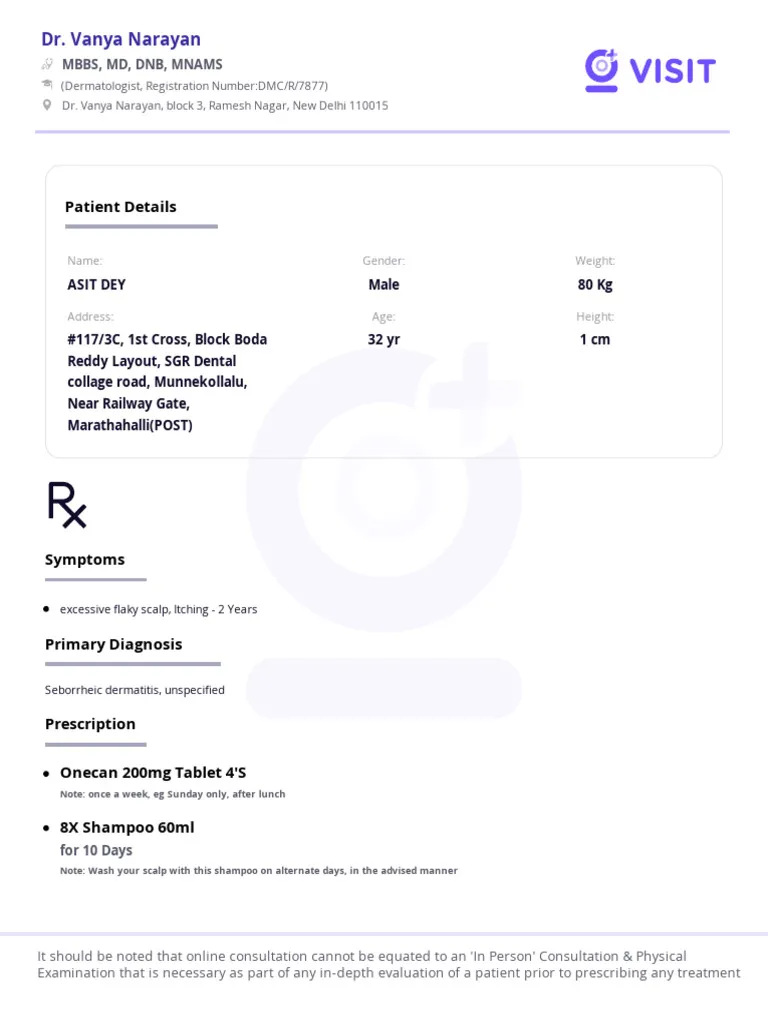
When Patients Do Their Own Homework: How Global Drug Approval Data Is Reshaping the American Doctor-Patient Conversation
Photo: RMHare, CC0, via Wikimedia Commons
For decades, the relationship between American patients and their physicians operated on a largely unspoken agreement: the doctor prescribes, the patient complies. That dynamic is shifting—and international pharmaceutical databases are a significant reason why.
Across the United States, a quietly growing cohort of patients is logging onto platforms like the European Medicines Agency (EMA), the World Health Organization's essential medicines database, Japan's Pharmaceuticals and Medical Devices Agency (PMDA), and Health Canada's drug product database before, during, and sometimes immediately after their medical appointments. Their goal is not to diagnose themselves. It is to ask better questions.
The Information Gap That Sparked a Movement
The United States Food and Drug Administration (FDA) is widely regarded as one of the world's most rigorous drug regulatory bodies. Yet rigorous does not always mean first. In numerous documented cases, medications approved and widely prescribed in Europe or Canada have taken years—sometimes more than a decade—to receive FDA clearance, or have never been submitted for US approval at all.
This gap matters to patients. When a person living with a chronic condition discovers that a medication with a decade-long safety record in Germany or the United Kingdom is simply unavailable to them in America, the natural response is to ask why—and to bring that question directly to their physician.
Take the example of certain migraine-specific treatments and multiple sclerosis therapies that were available in European markets well before their US counterparts. Patients who accessed EMA approval records found not only that these drugs existed, but that their clinical trial data—often published in peer-reviewed international journals—pointed to favorable outcomes. Armed with printed summaries and digital screenshots, some of these patients successfully prompted their neurologists to explore compassionate use pathways or accelerated access programs.
What the Databases Actually Offer
For the uninitiated, the breadth of publicly available international pharmaceutical data can be surprising. The EMA's public assessment reports, for instance, provide detailed summaries of the scientific evidence behind every approved medication in the European Union. These documents are written for regulatory professionals but are accessible to anyone with an internet connection and a willingness to parse technical language.
Health Canada's drug product database allows users to search by active ingredient, identifying brand names and formulations that may differ from their American equivalents. Japan's PMDA publishes English-language review reports for many domestically approved drugs. The WHO's Model List of Essential Medicines, updated every two years, reflects global consensus on which medications offer the best balance of efficacy, safety, and cost-effectiveness.
For American patients navigating a healthcare system where a single brand-name drug can cost ten times its international equivalent, these resources represent more than academic curiosity. They represent leverage.
The Physician Perspective: Concern and Cautious Respect
Not all physicians welcome patients who arrive with printed EMA documents. Some doctors report frustration when patients conflate foreign approval with domestic availability, or when they misinterpret regulatory differences between healthcare systems as evidence of deliberate suppression.
"There's a meaningful difference between a drug being approved in Europe and a drug being appropriate for a specific patient in my office," one internal medicine physician practicing in the Midwest explained in a widely shared medical forum discussion. "Regulatory agencies operate in different contexts. What the EMA approves reflects European population data, European prescribing practices, and European healthcare infrastructure. That context doesn't always transfer."
This is a legitimate concern. Drug approval processes vary in their endpoints, their required trial sizes, and their post-market surveillance requirements. A medication approved in the EU on the basis of surrogate endpoints—measurable biological markers rather than direct clinical outcomes—may not yet have demonstrated the long-term efficacy data that US regulators require.
Yet many physicians acknowledge that informed patients, even imperfectly informed ones, tend to produce better clinical outcomes. When a patient understands why a particular medication was chosen over an alternative, adherence improves. When a patient feels heard in their concerns about side effects—concerns sometimes validated by international safety signals that haven't yet triggered FDA action—the therapeutic relationship strengthens.
"I've had patients bring me data from the EMA that I genuinely hadn't seen," admitted a rheumatologist based in the Northeast. "One patient with a rare autoimmune condition found a European approval for a biologic that was being used off-label here. That conversation led us to a treatment path that worked significantly better for her. I wasn't offended. I was grateful."
Real-World Cases Where Global Data Made a Difference
Beyond anecdote, there are documented instances where international pharmaceutical data has meaningfully influenced American patients' care trajectories.
In the area of anticoagulation therapy, some patients with atrial fibrillation have used foreign approval records to advocate for newer oral anticoagulants over older warfarin-based regimens—particularly in cases where their physicians had not yet updated their prescribing habits to reflect current international guidelines. In oncology, patients accessing clinical trial registries—including the EU Clinical Trials Register—have identified experimental protocols available abroad that their domestic oncologists were unaware of or had not considered.
The rise of rare disease communities has amplified this phenomenon considerably. Patients with conditions affecting small populations often find that the most current clinical evidence originates in European or Asian research centers. These communities have become sophisticated consumers of international regulatory data, translating approval documents, coordinating with patient advocacy organizations overseas, and presenting compiled evidence to their US specialists.
Navigating the Line Between Advocacy and Overreach
The empowered patient movement is not without its risks. Misreading regulatory data—confusing approval status with superiority, or overlooking the population-specific limitations of clinical trials—can lead patients toward unsafe decisions. Some have attempted to import unapproved medications based on foreign approval records, a practice that carries both legal and medical risks.
Healthcare professionals and patient advocates alike emphasize that international pharmaceutical databases are most valuable as conversation-starters, not as prescriptions. The goal is not to replace physician judgment but to enrich the dialogue that informs it.
Several US-based patient advocacy organizations now offer guidance on how to responsibly interpret foreign regulatory documents. Some academic medical centers have begun incorporating international drug approval literacy into patient education programs, recognizing that the global availability of pharmaceutical information is not a trend that will reverse.
A New Kind of Patient—and a New Kind of Appointment
The American healthcare consumer of 2024 is increasingly a globally informed one. International pharmaceutical databases have given patients a window into a world where the same molecule may carry a different name, a different price point, a different approval status, and sometimes a different safety profile depending on which side of an ocean you happen to live on.
That knowledge is neither inherently dangerous nor inherently liberating. Its value depends entirely on how it is used—with humility, with context, and in genuine partnership with qualified medical professionals.
What is clear is that the old model of passive prescription acceptance is giving way to something more collaborative. Whether that evolution improves outcomes on a population level remains to be studied rigorously. But for the patients who have used a foreign approval record to open a door their domestic physician hadn't considered, the answer already feels self-evident.